
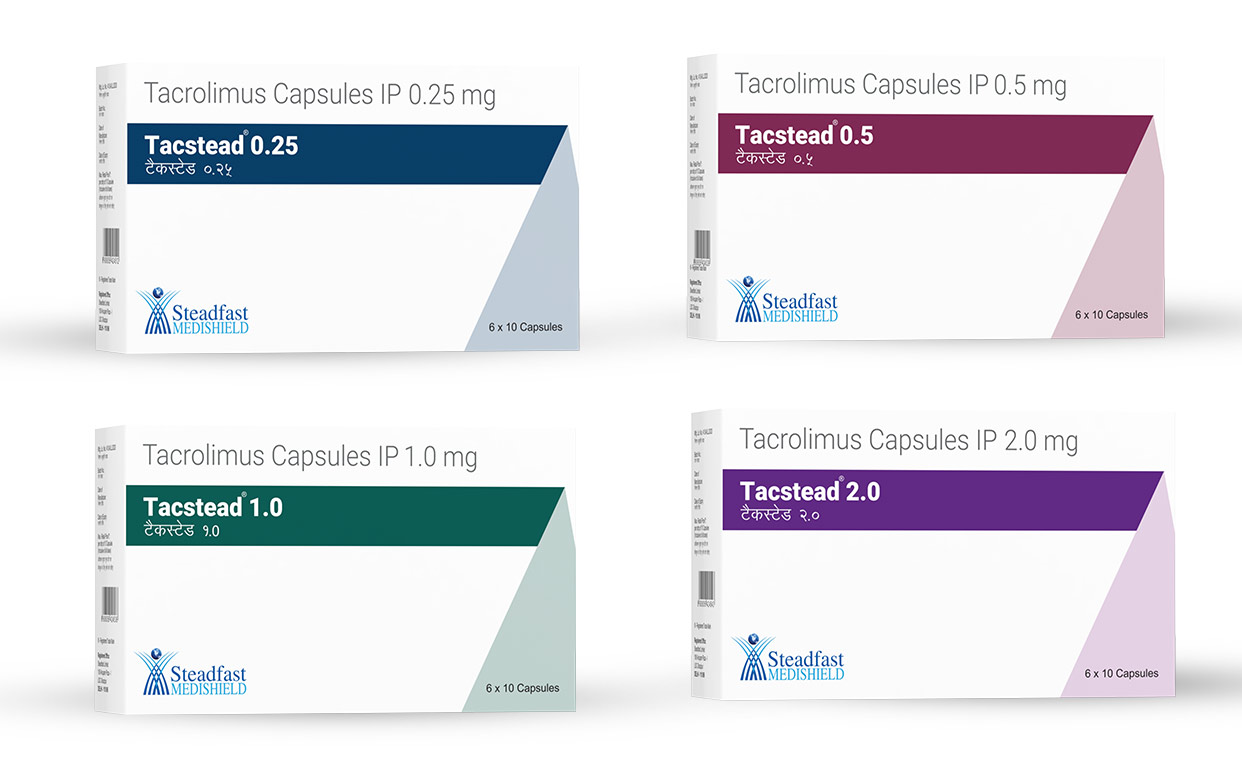
For the use of a Registered Medical Practitioner, Hospital or Laboratory only.
1. Description
Tacstead contains tacrolimus, a macrolide lactone with potent immunosuppressive activity, isolated from Streptomyces tsukubaensis. Tacrolimus is a macrolide immunosuppressant produced by Streptomyces tsukubaensis. Tacrolimus has an empirical formula of C44H69NO12, H2O and a formula weight of 822.05.
2. Composition
Each hard gelatin capsule contains:
- Tacstead 0.25 – Tacrolimus IP ….. 0.25 mg
- Tacstead 0.5 – Tacrolimus IP ….. 0.5 mg
- Tacstead 1.0 – Tacrolimus IP ….. 1.0 mg
- Tacstead 2.0 – Tacrolimus IP ….. 2.0 mg
3. Dosage Form
Capsule
4. Pharmacology
Pharmacodynamics
Tacrolimus exerts potent inhibitory effect on T- lymphocyte activation. It binds to immunophilins FK506 binding proteins (FKBP-12) and a complex of FKBP-12, calcium, calmodulin and calcineurin is formed, inhibiting phosphatase activity of calcineurin. This prevents dephosphorylation and translocation of nuclear factor of activated T – cells (NF-AT) and inhibits transcription of early T-cell activation gene, Interleukin-2, Tumour Necrosis Factor (TNF-α) and proto-oncogenes; suppressing expression of IL-2 and IL-7 receptor. This results in inhibition of T-lymphocyte activation. Tacrolimus also inhibits the mixed lymphocyte reaction, generation of cytotoxic T-cells and T-cell dependent B-cell activation.
Pharmacokinetics
Due to intra subject variability in its pharmacokinetics, individualization of dosage regimen is necessary.
Absorption
The absorption of Tacrolimus after oral administration is incomplete and variable with absolute bioavailability of 17 ± 10% in adult kidney transplantation, 22 ± 6% in adult liver transplantation and 18 ± 5% in healthy volunteers.
Food appears to reduce the absorption and relative bioavailability of Tacrolimus. In most cases, Cmax is achieved after 0.5 to 1 hour. However, the overall mean time to Cmax is about 2 hrs.
Distribution
Tacrolimus is 72 – 99% plasma protein bound over a concentration range of 5-50 ng/mL. At concentration above 50 ng/mL, the plasma protein binding becomes saturable. It also binds to erythrocytes and lymphocytes. The distribution of Tacrolimus between whole blood and plasma depends on several factors, such as haematocrit, temperature at the time of plasma separation, drug concentration and plasma protein concentration.
Metabolism
Tacrolimus is extensively metabolized by the mixed-function oxidase system, primarily the cytochrome P450 system (CYP3A). A metabolic pathway leading to the formation of eight possible metabolites has been proposed. Demethylation and hydroxylation were identified as the primary mechanisms of biotransformation in vitro. The major metabolite identified in incubations with human liver microsome is 13-demethyl Tacrolimus. In in-vitro studies, a 31-demethyl metabolite has been reported to have the same activity as Tacrolimus.
Elimination
In men, less than 1% of the dose administered is excreted unchanged in urine. After oral administration, faecal elimination is found to be 92.6 ± 30.7%, urinary elimination 2.3 ± 1.1% and the elimination half-life based on radioactivity is 31.9 ± 10.5 hours whereas it is 48.4 ± 12.3 hours based on Tacrolimus concentrations.
5. Indications
Tacrolimus is indicated for prophylaxis of organ rejection in patients receiving allogeneic renal or liver transplants.
6. Contraindications
Tacrolimus is contraindicated in patients with hypersensitivity to Tacrolimus.
7. Precautions
Warnings
- Administration of Tacrolimus may cause diabetes mellitus and may require treatment.
- Tacrolimus can cause neurotoxicity and nephrotoxicity when used in high doses.
- Tacrolimus should not be used simultaneously with Ciclosporin. Either of the two should be discontinued at least 24 hours prior to initiating the other
- Patients should be monitored closely for the evaluation of rejection, toxicity, dose adjustments and compliance.
- Mild to moderate hyperkalaemia may occur and may require frequent monitoring and treatment.
- Patients receiving Tacrolimus are at high risk of lymphomas, malignancies and infections due to over suppression of immune system. Therefore, combination immunosuppressant should be used with caution.
Precautions
Repeated laboratory tests like serum creatinine, potassium and fasting glucose should be assessed regularly. Routine monitoring of metabolic and haematological systems should be performed as clinically warranted.
General
- Mild to moderate hypertension is a common adverse effect. Anti-hypertensive therapy may be required in some patients.
- Patients with hepatic impairment: Lower dosage should be used in patients with compromised hepatic function.
- Patients with renal impairment: Lower dosage should be used in patients if graft becomes compromised.
- Hypertrophic cardiomyopathy: Hypertrophic cardiomyopathy has been observed in infants and children. Dosage reduction or discontinuation of therapy is required.
Pregnancy: There are no adequate and well-controlled studies in pregnant women. Tacrolimus should be used in pregnancy only if the benefits outweigh potential risks to fetus.
Nursing Mothers: Since Tacrolimus is excreted in human milk, nursing should be avoided.
8. Drug Interactions
As Tacrolimus is metabolized by cytochrome P450 CYP3A enzyme, potential drug interactions are numerous.
Increased Tacrolimus Blood Concentration: Calcium channel blockers, Antifungal agents, Macrolide antibiotics, Corticosteroids, Ciclosporin, Prokinetic agents, Omeprazole, Bromocryptine, Protease inhibitors, etc., increase blood concentration of Tacrolimus. Monitoring of blood concentration of Tacrolimus and dosage adjustment is recommended.
Decreased Tacrolimus Blood Concentration: Anticonvulsants, Anticoagulants, Antacids, Rifabutin and Rifampicin decrease Tacrolimus blood concentration. Interaction studies with drugs used in HIV therapy have not been conducted.
Increased Renal Toxicity: Nephrotoxic drugs like Acyclovir, Aminoglycosides, Amphotericin B, ACE inhibitors, Cisplatin, Ciclosporin and NSAIDs have a potential for additive or synergistic toxicity with Tacrolimus. Care should be taken when these drugs are co-administered with Tacrolimus.
Vaccines: Tacrolimus may reduce the efficacy of vaccines and recipients of Tacrolimus should not receive live attenuated vaccines.
Food: Food decreases the rate and extent of absorption of Tacrolimus. Absorption for this drug is the greatest under fasted conditions. Grapefruit juice is reported to increase Tacrolimus blood through concentration and should be avoided.
9. Adverse Effects
Tacrolimus shows adverse events common to other immunosuppressive therapies viz. neurotoxicity, nephrotoxicity, increased risk of infection and malignancy, diabetes mellitus and a lymphoproliferative disorder related to Epstein-Barr virus. The most common adverse events reported are:
- Nervous system – Tremor, Headache, Paresthesia, Dizziness, Insomnia, Seizures, Coma and Delirium with high plasma concentrations of Tacrolimus
- Gastrointestinal – Diarrhoea, Constipation, Nausea, Vomiting and Dyspepsia
- Cardiovascular – Hypertension and Chest Pain
- Urogenital – Creatinine increase and Urinary tract infection
- Metabolic and Nutritional – Hyperkalaemia, Hyperglycaemia (new onset post-transplant diabetes mellitus), Hyperlipidaemia, Hypophosphataemia, Hypomagnesaemia, Hyperglycaemia, Diabetes mellitus, Hypokalaemia and Oedema
- Haemic and Lymphatic – Anaemia and Leucopenia
- Respiratory System – Dyspnea
- Musculoskeletal – Arthralgia and Back Pain
- Skin – Rash and Pruritus
- Miscellaneous – Infection, Peripheral oedema, Asthenia, Abdominal Pain and Fever
10. Dosage & Administration
In Renal Transplantation: Tacrolimus oral therapy should be started as soon as a patient is able to tolerate oral dose, at a dosage of 0.2 mg/kg/day in adults as 2 divided doses taken every 12 hrs. The initial dose of Tacrolimus may be administered within 24 hours of transplantation, but preferably until renal function has recovered. The recommended target whole blood trough concentrations is between 7-20 ng/mL for 0-3 months and 5-15 ng/mL for 4-12 months. Paediatric patients may require higher dosage.
In Liver Transplantation: Tacrolimus therapy should be started at oral dose of 0.10 – 0.15 mg/kg/day administered in two divided daily doses every 12 hrs. Most patients are stable when whole blood trough concentrations are maintained between 5-20 ng/mL. Dosage adjustments are made on the basis of clinical assessment of rejection, tolerability and on blood concentration of Tacrolimus.
Replacement/Concomitant Administration with Ciclosporin: Tacrolimus and Ciclosporin should not be administered concomitantly. Either of the two should be discontinued at least 24 hours before initiating the other.
Adjunct Therapy: Concomitant use of corticosteroids and other immunosuppressants such as Mycophenolate mofetil or Azathioprine is recommended during early post-transplant. However, lower maintenance doses of steroid are required due to steroid sparing effect of Tacrolimus.
Blood Concentration Monitoring: Monitoring of Tacrolimus blood concentrations in conjunction with other laboratory and clinical parameters is considered an essential aid to patient management for the evaluation of rejection, toxicity, dose adjustments and compliance. Factors influencing frequency of monitoring include, but are not limited to hepatic or renal dysfunction and addition or discontinuation of potentially interacting drugs and the post-transplant time. Blood concentration monitoring is not a replacement for renal and liver function monitoring and tissue biopsies. Whole blood is the matrix of choice and specimens should be collected into tubes containing ethylene diamine tetra acetic acid (EDTA) anti-coagulant. Heparin anti-coagulant is not recommended because of the tendency to form clots on storage.
11. Overdosage
There is a very limited experience of Tacrolimus overdose. Acute overdosage does not show any special adverse effect. However, it is expected that they shall be consistent with reported adverse effects of Tacrolimus. Overdose Management: It is expected that Tacrolimus is not dialysable to any significant extent. Although, the use of charcoal is reported, it is not supported by experience. General supportive measures and treatment of specific symptoms should be followed in all cases.
12. Storage
Store in a dry place at a temperature not exceeding 30°C. Protect from light. Keep the medicine out of reach of children.
Additional Information
Special Populations
Paediatric: Following oral administration mean AUC and Cmax are 337 ± 167 ng/hr/mL and 43.4 ± 27.9 ng/mL, respectively. The absolute bioavailability was 31 ± 21%. Paediatric patients needed higher doses than adults to achieve similar Tacrolimus trough concentrations.
Renal and Hepatic Insufficiency: The mean clearance of Tacrolimus in patients with renal dysfunction is similar to that in normal volunteers. The mean clearance of Tacrolimus in patients with mild hepatic dysfunction is not substantially different from that in normal volunteers.
Race: A retrospective comparison of Black and Caucasian kidney transplant patients indicate that Black patients require higher Tacrolimus doses to attain similar trough concentrations.
Gender: There is no effect of gender on pharmacokinetics of Tacrolimus in the kidney transplant.
13. Presentation
- Tacstead 0.25 mg – 10 capsules in a strip, 6 strips in a Box.
- Tacstead 0.5 mg – 10 capsules in a strip, 6 strips in a Box.
- Tacstead 1.0 mg – 10 capsules in a strip, 6 strips in a Box.
- Tacstead 2.0 mg – 10 capsules in a strip, 6 strips in a Box.